The Complete Guide to Vitamin D and Skin as Daylight Fades
Quick Answer: Above roughly 35 degrees latitude, UVB intensity falls below the threshold for meaningful vitamin D synthesis for several months of the year - in much of the northern United States and Europe, from around October to March. Your skin is where that synthesis happens, and vitamin D also has genuine roles in keratinocyte differentiation, skin barrier function and the innate immune peptides in skin. That said, most of the dramatic skin claims made for vitamin D are unsupported. What the evidence does support: correcting a deficiency matters, food sources are limited, supplementation in the 600 to 800 IU range is standard for most adults, and more is not better. This is general information, not medical advice.
Every autumn the same articles appear promising that vitamin D will transform your skin.
Here is the honest version: what actually happens as daylight fades, what the skin evidence supports, and what to do about it.


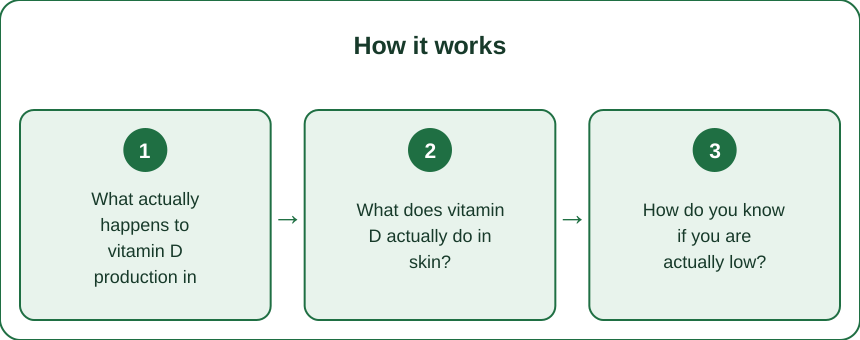
What actually happens to vitamin D production in autumn?
It stops, at a fairly precise point, and it is a matter of angle rather than warmth.
Vitamin D synthesis in skin requires UVB radiation in a narrow wavelength band, roughly 290 to 315nm. UVB is filtered by the atmosphere in proportion to how much atmosphere it has to pass through, which depends on the sun’s angle above the horizon.
When the sun is below roughly 45 degrees elevation, UVB intensity drops sharply. Below about 30 degrees, effectively no vitamin D synthesis occurs.
The consequence is a vitamin D winter - a period each year when no amount of outdoor time produces meaningful vitamin D. Above about 35 degrees latitude, that period runs from roughly October to March, and it is longer the further north you go. In northern Britain and the northern United States it can extend six months.
Crucially, it has nothing to do with temperature. A bright, cold, clear January day at high latitude produces no vitamin D. A cloudy day in June produces some. People consistently misjudge this because they use warmth and brightness as a proxy for UVB, and neither is.
Even within the season, the daily window is narrow - roughly the middle of the day, when the sun is highest. Morning and late afternoon exposure in spring and autumn contribute very little.
And there are large individual differences. Melanin absorbs UVB, so people with darker skin require considerably longer exposure to produce the same amount - a well-documented reason for higher deficiency rates in people with more pigmented skin at higher latitudes. Age matters too: the skin’s capacity for synthesis declines meaningfully with age.
All of which means autumn is when stored vitamin D starts being drawn down, and levels typically bottom out in late winter.
What does vitamin D actually do in skin?
More than most nutrients, and less than the marketing claims.
Skin is unusual: it is both the site of vitamin D synthesis and a target tissue with its own vitamin D receptors.
Keratinocyte differentiation is the best-established role. Vitamin D signaling influences how skin cells mature as they move toward the surface, which is fundamental to forming a functional barrier. This is why vitamin D analogues are an established treatment for psoriasis, a condition characterized by disordered keratinocyte proliferation - one of the clearest clinical demonstrations of the pathway.
Barrier function follows from that. Vitamin D signaling contributes to the production of barrier components, and there is reasonable evidence linking vitamin D status to skin barrier integrity.
Innate immunity in skin is a genuine one. Vitamin D upregulates antimicrobial peptides including cathelicidin, which are part of the skin’s first-line defense. This is one of the more mechanistically solid links and is thought to underlie some of the association between vitamin D status and atopic dermatitis severity.
Where the evidence is weaker: claims about vitamin D reducing wrinkles, improving skin tone, or acting as a general anti-aging intervention are largely extrapolation rather than demonstration. There are plausible mechanisms and very little good clinical data.
And topical vitamin D in cosmetics is a different question from vitamin D status. Prescription analogues have real effects in specific conditions; over-the-counter cosmetic formulations are not the same thing and are not well supported.
The honest summary: vitamin D matters for skin, correcting a deficiency is worth doing, and it is not a cosmetic treatment.
How do you know if you are actually low?
A blood test, because the symptoms are non-specific and self-assessment does not work.
The measured marker is serum 25-hydroxyvitamin D, which reflects both dietary intake and cutaneous synthesis and has a half-life long enough to represent status over weeks.
Thresholds vary between organizations, which is a genuine source of confusion. Broadly, deficiency is commonly defined below 30 nmol/L (12 ng/mL), insufficiency in a band above that, and sufficiency generally accepted above 50 nmol/L (20 ng/mL). Some bodies use higher targets, and the disagreement is real rather than something you can resolve by reading more articles.
Symptoms are unhelpful for self-diagnosis. Fatigue, low mood, muscle aches and general malaise are all associated with deficiency and also with a hundred other things - including simply being in autumn.
Risk factors are more useful than symptoms. Higher risk includes: living at higher latitude, darker skin, limited outdoor time, consistent full sun protection, older age, obesity - vitamin D is fat-soluble and sequestered in adipose tissue - malabsorption conditions, and certain medications.
Skin-specific signs are not reliable indicators. Dry skin in autumn is far more likely to be low humidity and hot showers than vitamin D status.
If you have several risk factors, testing is reasonable and it is the only way to know. If you have none and you eat a varied diet, the standard maintenance recommendation is a reasonable default without testing.
This is general information, not medical advice.

What are the actual food sources?
Few, and they matter more in the months when your skin cannot make any.
Oily fish is by far the best food source. Salmon, mackerel, sardines and herring contain meaningful amounts - a portion of salmon can provide a substantial fraction of a day’s requirement, though wild and farmed differ considerably.
Cod liver oil is very high and also very high in vitamin A, which has its own upper limit - worth knowing before taking it daily.
Egg yolks contain modest amounts, varying with the hen’s diet and outdoor access.
UV-exposed mushrooms are the notable plant source. Mushrooms produce vitamin D2 when exposed to UV light, and some commercially available mushrooms are deliberately UV-treated. Ordinary mushrooms grown in the dark contain very little.
Fortified foods do much of the work in practice in countries where fortification is common - milk and plant milks, some cereals, some spreads. Fortification levels vary enormously by country, which is why general advice translates poorly across borders.
The realistic assessment: for most people, food alone does not reach typical recommended intakes during the vitamin D winter unless oily fish is eaten several times weekly. This is precisely why many public health bodies recommend supplementation during autumn and winter rather than relying on diet.
Vitamin D is fat-soluble, so absorption improves when taken with a meal containing some fat - a small practical detail that is easy to get right and easy to overlook.
Myth vs Fact: Vitamin D and Skin
Myth: Sitting by a window gives you vitamin D. Fact: Standard window glass blocks essentially all UVB. You can get warm, get UVA exposure and get no vitamin D at all. This applies to conservatories, cars and offices.
Myth: Sunscreen causes vitamin D deficiency. Fact: In laboratory conditions sunscreen substantially reduces synthesis, but real-world studies consistently find that typical sunscreen use does not cause deficiency - largely because people apply less than the test amount and miss areas. The skin cancer risk of skipping sunscreen is a much clearer harm than the vitamin D benefit of doing so.
Myth: If some is good, more is better. Fact: No. Vitamin D toxicity is real, causes hypercalcemia, and results almost exclusively from high-dose supplementation rather than sun or food. There is a defined upper limit and very high doses have not shown additional benefit in most outcomes studied.
Myth: Tanning beds are a reasonable vitamin D source. Fact: They are classified as carcinogenic to humans. Whatever vitamin D they produce is available far more safely from a supplement costing a few cents a day.
Myth: Vitamin D will clear my acne or fix my eczema. Fact: There are associations between low vitamin D status and severity in some inflammatory skin conditions, and correcting a deficiency may help. That is different from vitamin D being a treatment. For an established skin condition, see a dermatologist - vitamin D correction is a reasonable adjunct, not a plan.
Myth: You can catch up in summer and coast through winter. Fact: Partly true - stores do carry over, which is why levels decline through autumn rather than crashing. But for most people at higher latitudes those stores are exhausted well before spring, which is why late winter is when levels are lowest.
What should you actually do this autumn?
Take the standard maintenance dose, get midday light while it still counts, and treat skin dryness as a separate problem.
Supplementation is the practical answer for most people at higher latitudes. Common public health guidance suggests around 400 to 800 IU (10 to 20 micrograms) daily for most adults during autumn and winter, with several countries recommending it for the whole population during those months. Higher doses should be based on a blood test and clinical advice, not on internet defaults.
D3 is generally preferred over D2 - it appears somewhat more effective at raising and maintaining serum levels, though both work.
Take it with a meal containing fat.
Get outdoor midday light while it still produces anything, which in early autumn it still does. Beyond vitamin D, daylight exposure has independent benefits for circadian rhythm, sleep and mood that persist through the months when synthesis has stopped - so the habit is worth keeping regardless.
Do not confuse vitamin D with the actual cause of autumn skin problems. The dryness, tightness and flaking that arrive with the heating are caused by low indoor humidity, hot showers, and increased transepidermal water loss. Those are solved with a humidifier, shorter cooler showers and a better moisturizer - not with a supplement.
Get tested if you have risk factors, particularly darker skin at higher latitude, very limited outdoor time, malabsorption conditions, or if you are considering anything above standard maintenance doses.
And keep expectations calibrated. Correcting a genuine deficiency can produce real improvements in wellbeing, muscle function and possibly skin barrier health. Taking vitamin D when you are already replete will do essentially nothing, which is the most common way people are disappointed by it.
This is general information, not medical advice. Discuss supplementation with a clinician, particularly during pregnancy, if you take other medications, or if you have kidney disease or a condition affecting calcium metabolism.
FAQ: Vitamin D and Skin Questions, Answered
How much sun would I need in summer to build up stores?
Estimates vary widely with skin tone, latitude, time of day and how much skin is exposed - which is precisely why no single number is reliable. The general shape of the guidance is short, frequent, midday exposure of arms and legs, well short of any redness. Burning provides no additional vitamin D and carries clear risk. In autumn and winter above about 35 degrees latitude, no amount of exposure works, which is when the question becomes moot.
Will taking vitamin D make my skin less dry this winter?
Probably not, unless you are genuinely deficient. Winter skin dryness is overwhelmingly driven by low indoor humidity, hot water and barrier disruption, and it responds to environmental and topical changes rather than to a supplement. Correcting a real deficiency may help barrier function modestly, but it is not the lever for typical winter dryness.
Is it worth testing, or should I just supplement?
If you would take the standard maintenance dose either way and you have no particular risk factors, testing changes nothing and you can skip it. Testing becomes worthwhile if you have multiple risk factors, if you have symptoms you want explained, or if you are considering a dose above standard maintenance - because at that point you need to know your starting point.
Does vitamin D help with seasonal low mood?
The association between low vitamin D and low mood is well documented; the evidence that supplementation treats seasonal affective disorder is much weaker and inconsistent. Light exposure, particularly bright morning light, has considerably better support for seasonal mood changes. Correcting a deficiency is worth doing on its own merits, but it is not a substitute for light or for treatment where treatment is needed.
TL;DR:
- Above about 35 degrees latitude, vitamin D synthesis stops from roughly October to March - it is about sun angle, not warmth or brightness.
- Skin is both the factory and a target tissue - vitamin D has real roles in keratinocyte differentiation, barrier function and antimicrobial peptides.
- The cosmetic anti-aging claims are extrapolation, not evidence.
- Symptoms cannot tell you your status. Risk factors and a blood test can.
- Food rarely covers it in winter without oily fish several times a week - which is why supplementation is standard public health advice.
- 400 to 800 IU daily with a fat-containing meal is the usual maintenance range; higher doses need a test and clinical advice.
- Winter skin dryness is humidity and hot showers, not vitamin D. Fix that separately.
This is general information, not medical advice. Correcting a deficiency helps; topping up when you are already replete does not.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
